Showing posts with label Rohan. Show all posts

Wednesday, 11 November 2015

Ever Wondered How Alcohol Affects the Nervous System?

Not only in the UK, but all around the world, alcohol is enjoyed by many - drinking is indeed a popular pastime. However, when individuals over-indulge, it can lead to serious health problems including addition even though this is not very common. Nevertheless, in the UK, the NHS estimates that '9% of men and 4% of women show signs of alcohol dependence' (Source: DrinkAware). Over the decades, interest has increased around the effects of alcohol, not only on the physical but also on the mental state. In medicine, researchers will endeavour to find a physiological mechanism to a unexplained mental or behavioural phenomenon. A perfect example of this is the effect of various drugs, illegal and legal, on human behaviour. Quite a few of these substances cause imbalances in the amount of neurotransmitter released from pre-synaptic vesicles into the synaptic cleft in particular areas of the brain. In turn, the frequency of electrical impulses transmitted can fluctuate which can ultimately influence behaviour. To understand this better, it is beneficial to look back in history when the basic physiology and chemistry were uncovered.

Above: Scanning electron micrograph of neurotransmitter-containing vesicles (orange and blue) being released from a pre-synaptic neuron (Source: AnatomyBox)


Pre-1930s, there were noticeable disagreements between academics on how exactly neurons communicate their signals to one another. Was it electrical or was it chemical? It wasn't until 1936, when Sir Henry Dale and Otto Loewi received the Nobel Prize in Physiology or Medicine, that it became clear that these signals were indeed due to chemical transmission. This is possible through the action of neurotransmitters - chemicals which are released into the space between neuron, the synaptic cleft. Some scientists prior to this award did suggest that chemicals were involved, through observing the similarities in nerve stimulation in plants and animals (Source: NobelPrize.org) Loewi managed to illustrate the importance of these chemicals in an elegant way using experiments on frogs. His papers were published in 1921 - these showed that nerve impulses affected the heart using chemical transmission. Firstly, Loewi stimulated the vagus nerve fibres of an isolated frog's heart that had been connected on the other side to a ringer solution. Soon after this, he observed that the strength and frequency of the heartbeat decreased. The fluid remaining was used to surround another frog heart - the vagus nerves were not electrically stimulated. This time, the heart changed it's activity as if it had been electrically stimulated (Source: AnimalResearch.info) It seemed that the fluid has caused this change. Dale's discovery of the action of acteylcholine was inline with Loewi's results and so after subsequent years of research, Dale and Loewi were awarded the Nobel Prize in Physiology or Medicine. 

Chemical transmission is an important concept to understand when we consider how an impulse is able to transmit from neuron to neuron in the brain. It can be understood as a cascade of events beginning with the arrival of an action potential at the axon terminal of the pre-synaptic neuron. The depolarisation stimulates calcium ion channels to open, causing an influx of Ca2+ into the axon. This in turn stimulates vesicles filled with neurotransmitter to migrate to the end of the axon. The vesicles are then able to fuse with the lipid bi-layer membrane to release the neurotransmitter (e.g. acetylcholine) into the synaptic cleft. When these neurotransmitters bind to ligand-gated sodium channels on the post-synaptic neuron, this triggers another action potential to fire. To prevent constant firing of action potentials, a neurotransmitter such as acetylcholine is broken down by an enzyme (in this case, acetylcholinesterase), and the inactive products are reabsorbed by the pre-synaptic neuron through re-uptake transporters. These events will become important when we look at the effect of alcohol on the nervous system.

Above: Schematic diagram showing the transmission of an action potential  (Source: Biological Sciences Review Volume 26, Number 2).

Now, alcohol is one of the few substances than can cross what is referred to in anatomy as the blood-brain barrier (BBB). This is largely a fatty barrier than surrounds the blood vessels in the brain. In medical research, this barrier has been notoriously difficult to overcome when delivering drugs or attempting to treat an array of brain-related diseases, for example Alzheimer's. Until very recently, this has caused problems, however scientists have now found a way of delivering cancer-fighting drugs to targets by breaching the blood-brain barrier. A research team in Canada used 'tiny gas-filled bubbles, injected into the bloodstream of a patient, to punch temporary holes in the blood-brain barrier'. Following this, ultrasound was used to make the bubbles 'vibrate and push their way through, along with chemotherapy drugs' (Source: BBC) This has been a significant breakthrough - I encourage you to read more on the subject here.

The reason that alcohol is able to cross this barrier is that it is lipid soluble. Once alcohol crosses the barrier, it is able to affect the action of neurotransmitters. Before looking at how alcohol comes into play, it is useful to consider the different types of neurotransmitter that exist in the nervous system, and their different modes of action.

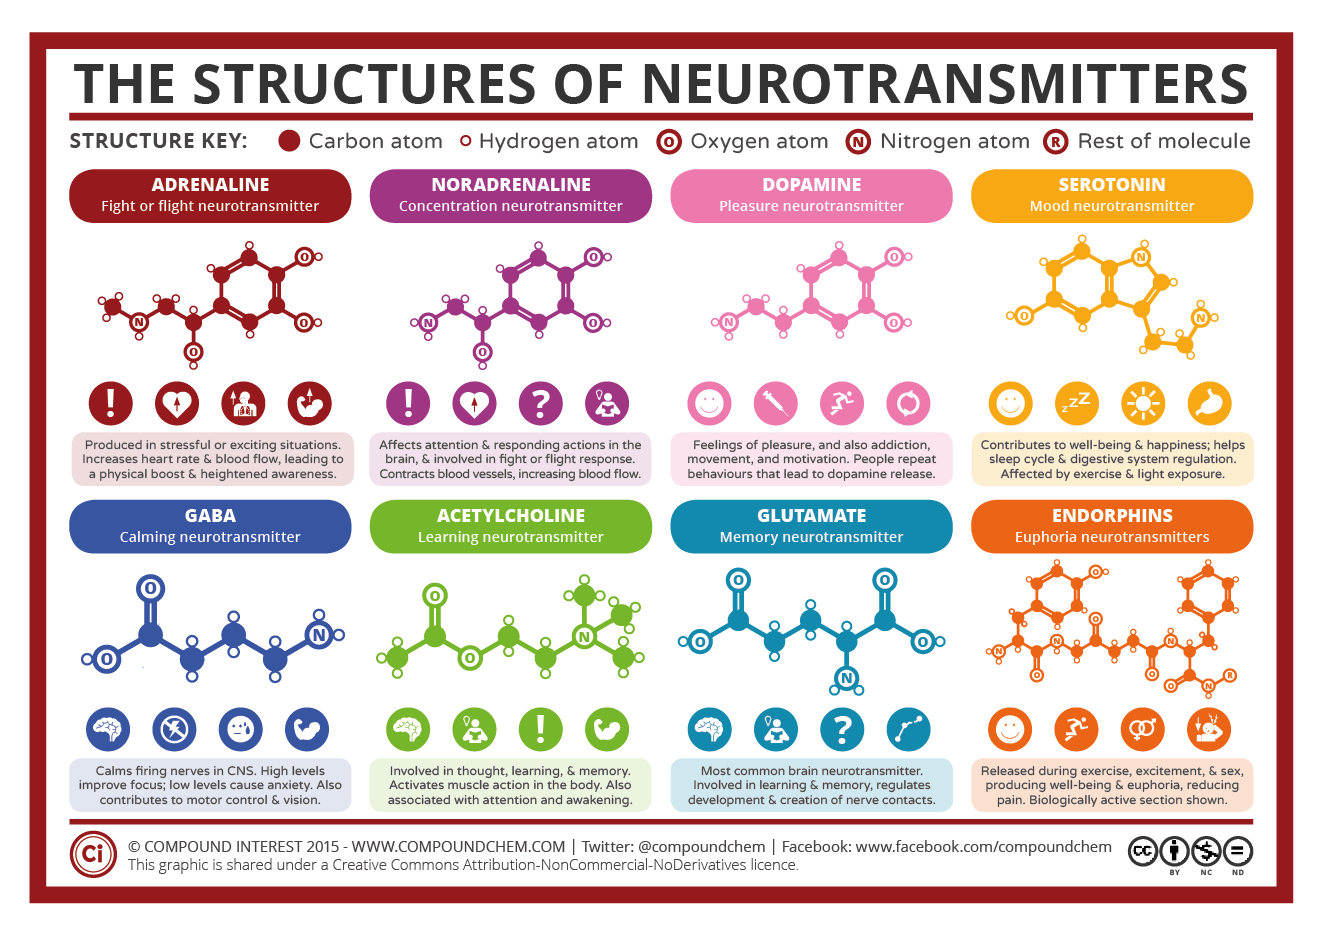
Neurotransmitters can either be excitatory (increases the likelihood of an action potential being fired on the post-synaptic neuron) or inhibitory (decreases the likelihood). Examples of excitatory neurotransmitters are glutamate, dopamine and acetylcholine. Glutamate is the most common kind of neurotransmitter in the brain and is thought to be involved in memory and learning. The well-known neurotransmitter dopamine is involved in the mechanisms of motivation and reward. It follows that many addictive drugs utilise the 'feel good' sensation that dopamine causes. And finally, acetylcholine is most commonly used in the contraction of involuntary muscle - it can be released at the site of a neuromuscular junction. A good example of an inhibitory neurotransmitter is gamma-amino butyric acid (GABA) - it's action is known to reduce stress. In fact, about a third of all brain synapses use GABA, and anti-anxiety drugs such as Valium enhance it's action. Another example of an inhibitory neurotransmitter is the amino acid glycine, however this is used mainly in the spinal cord, and is involved in about half of all synapses there, the rest using GABA. (Source: Principles of Anatomy and Physiology 13th edition - G.J. Tortora and B. Derrickson)

Above: The structure of common neurotransmitters (Source: CompoundChem). See source link for larger image.


Alcohol is widely known as a depressant drug. It is able to decrease excitatory action, and increase inhibitory action. Here, we can look at how alcohol affects the release of GABA. Ethanol increases the amount of GABA neurotransmitter released from pre-synaptic neuron in the brain, by increasing the likelihood that GABA containing vesicles fuse with the bi-layer membrane. To further induce an effect, ethanol encourages GABA to bind more easily to it's corresponding ligand-gated ion channels on the post-synaptic neuron. Subsequently, chloride ions flood into post-synaptic neuron cytoplasm, decreasing the chance that an action potential will fire. In parallel with this effect on GABA transmission, alcohol also affects the action of the excitatory neurotransmitter, glutamate. Ethanol decreases glutamate's excitatory activity, and this effect is quite dramatic considering that glutamate is used in 90% of synapses! (Source: Biological Sciences Review Volume 26, Number 2) The binding of glutamate to it's receptors on the post-synaptic neuron is blocked, thus an action potential cannot be triggered. Since glutamate is used in routes in the brain associated with learning and memory, it is common that people will suffer memory loss after a booze-fuelled night.

The imbalances between inhibitory and excitatory activity do explain the drowsiness, slow reactions and sometimes poor memory people have when drinking a significant amount of alcohol. However one observation we may have forgotten is that to many, drinking alcohol can make them feel good. From research, we know that the reward centre and the pathways associated with it are located in an area of the brain called the striatum. So far, there has been no clear link between alcohol and an effect on the action of the neurotransmitter dopamine. Recall that dopamine is involved in motivation and reward. Where is the link? Well, it is thought that the reward feedback system is usually 'kept in check by GABA inhibition. When this inhibition is suppressed, the reward system becomes more active'. Remember that alcohol does cause suppression of GABA inhibition as it encourages more GABA to bind to the post-synpatic neuron!

Above: Schematic of the brain showing the location of the striatum (yellow-orange region) (Source: Biological Sciences Review Volume 26, Number 2)

To conclude, we can see that in order to understand how alcohol can affect the nervous system, it is important to appreciate the biological cascade of events that occur during chemical transmission at the synapse. Although alcohol can be enjoyed in moderation, the public must be aware of the potential health complications associated, including liver disease, weight gain and sleep disruption. The incidence of liver disease particularly, is rising in the UK. Bear in mind that this disease not only affect adults, but also the young as well. Let us not forget also of the societal problems that can arise due to alcohol abuse, which include antisocial behaviour and violence in extreme cases.

Even today, alcohol still presents unsolved mysteries to researchers. However with continuous advances in technology, medicine, and neuroscience, how the brain is affected by substances is becoming clearer and clearer.


Additional credit: Oliver Freeman is a writer for the Biological Sciences Review and is also studying for a PhD in neuroscience.
 - Michelle Roberts, for her article published on the BBC website, 'Scientists breach brain barrier to treat sick patient'. Read more on the subject here.

Saturday, 7 November 2015

Revolutionary Platinum-based Chemistry: A New Hopeful for Cancer Therapy

As many would agree, one of the most well-known treatments that cancer patients undergo is chemotherapy. Today, it is not unusual for platinum compounds to be used in chemotherapy - cisplatin is a notable example.


Above: False-colour electron micrograph of cancer cells (Source: Wellcome Collection)


In medicine, particularly pharmacology, the shape of molecules are extremely important. In cisplatin, the oxidation state of platinum is +2 and the molecule is said to be square planar. This means that all of the atoms lie in the same plane, forming a square if you were to join up the atoms with imaginary lines. Each of the groups, Cl- (Chloride - with an oxidation state of -1) and NH3 are called ligands, and because each of the different groups are on the same side of the molecule, the platinum compound is said to have a cis structure. In the body, cisplatin's basic chemistry works as follows:

Since, in the bloodstream there is a high concentration of chloride ions, none of the ligands on the molecule are substituted (NH3 groups are more resistant to this substitution). However, once inside the cell the environment is very different. In fact, there is a much lower concentration of chloride ions, and the chloride ligands are replaced by water molecules. Now the cisplatin compound is activated. This is a perfect illustration of Le Chatelier's principle:

"If a dynamic equilibrium is disturbed by changing the conditions, the position of equilibrium moves to counteract the change"
(Source: Chemguide)

Above: Displayed formula of cisplatin


Although cisplatin  has proved effective, over the years, several similar drugs such as carboplatin have been produced to maximise efficiency and potency. The drug works by disrupting cell replication, thus leading to cell apoptosis (death). The mechanism for this relies on the substitution of those chloride ligands for water molecules once inside the (cancer) cell. From this point, nitrogen atoms from the nucleotides forming DNA substitute the water molecules. Water molecules tend to be easily replaced. In this situation, cisplatin  is effectively bound to the DNA, causing the nucleotide chain to bend due to formation of a 'kink'. In DNA replication, the shape of DNA is very important and many checks are made by feedback mechanisms to make sure the cell has proceed to divide by mitosis. Once cisplatin is bound, mitosis can no longer take place - cell death results.

However, current research into the field of photoactive compounds has proved promising - the research could be a step to producing cancer drugs that can be activated at the tumour site using lasar technology. Firstly, let us consider the properties of platinum. It has a silverly coloured surface (without tarnish) and is used in catalysis - catalytic converters in road vehicles is an example. So why does this metal prove useful in the body? Platinum is considered a relatively safe, it is said to be biologically compatible due to it's inability to react with body tissue. However, in medicine, what we are more concerned about is whether we can use platinum compounds. In fact, these compounds are used but scientists are aware of the toxicity of such substances. Platinum ions that are bonded to several ligands help to channel potential toxicity in a useful way, often to produce life-saving drugs.

The challenge now is to produce treatments that are even more localised to the cancer cells. This is inevitably the subject of research in universities and pharmaceutical corporations across the globe. Existing cancer drugs work well simply because cancer cells are subject to more damage than normal body cells - cancer cells proliferate at a faster rate. Note however that normal body cells can still become affected. As many may have experienced, the side effects of chemotherapy can be quite extensive, nausea and kidney damage to name a couple. The human body is simply trying to reject the foreign substance introduced, and this is what drives scientists to look for new solutions. 

The key fact to know is that whilst cisplatin and other similar drugs are not tumour specific, how they are activated can be controlled. Platinum, like many other transition metals, have multiple oxidation states. Platinum(IV), Pt4+ complexes 'have been proven to be inactive and non-toxic inside cells, but only in the dark' (Source; Chemistry Review Volume 24, Number 4). One reason for this is to do with the shape of these platinum(IV) complexes. With an oxidation state of +4, platinum is able to form 6 bonds to ligands in an octahedral arrangement. Remember than a platinum(II) compound can only form 4 bonds with ligands in a square planar structure. This higher oxidation state enables the molecule to be less reactive and therefore ligands tend to be become replaced. This is very relevant, recall that cisplatin has it's chloride ion ligands replaced by water molecules once inside the cell. However, it is important to remember that the reduced reactivity in the case of platinum(IV) compounds is true in the dark. These compounds can be photo-activated - light enables the configuration of the molecule to change. This process is irreversible:

Above: The photo-activation of a platinum complex - X and Y denote alternative ligands (Source: Chemistry Review Volume 24, Number 4)

This reaction is able to occur to due to the phenomenon of electron transition. An election which absorbs light energy is able to be promoted to a higher energy state, and therefore a higher energy orbital with an atom. In transition metal chemistry, it is common knowledge that when ligands bond to the central metal ion, this causes the d-orbitals of the metal ion to split. The orbitals are split into two levels, one with a higher energy level than the other. The very fact that these complexes can absorb light energy means that transition metal complexes are often colourful. During the above reaction, electrons in the central metal ion 'jump' to a higher energy level. Any remaining light that is not absorbed is reflected back. These electron transitions can cause multiple changes, such as a change in oxidation state of the central ion, or substitution of ligands. Controlling this activation could indeed be a useful tool in cancer therapy, it could potentially have wider applications in medicine. After activation, the cisplatin-like compound can then perform it's anti-cancer wonders. 

Above: Diagram showing that the energy of a particular wavelength of light is equal to the energy required to promote an election to a higher energy level (Source: Chemguide)


Using these platinum compounds does leave room for flexibility. For example, scientists would be able to change the ligands to vary the amount of light energy absorbed (to cause d-orbitals to split). However, getting this energy quota just right is a challenge, and is still the subject of research. 

So what are the applications in cancer treatment? Any treatments should be as safe as possible, so it is important what type of light should be used to activate the platinum complexes inside the body. Now, most complexes tend to be activated by blue or even UV light, however these frequencies of light do not penetrate tissue as well as red light does. Bear in mind that UV can damage tissue - red light seems a relatively safe option. A compromise must be made as red light would mean that it is less likely that a complex would be activated. Nonetheless, 'some promising Pt4+ complexes have been made, which are non-toxic in the dark but once activated have a high toxicity towards cancer cells'. After all, it is completely dark inside the body, therefore a laser would need to be used to activate the chosen drug. A laser would be a suitable choice due to it's precision - it would be much less likely that a healthy body cell would be affected (Source: Chemistry Review Volume 24, Number 4). 

As with any new treatment, this new concept would need to be subject to vigorous testing through a series of clinical trials. Safety and effectiveness are two crucial criteria that will need to be evaluated during the course of these trials in future. 

Additional credit: Louise Tear who wrote an article in the Chemistry Review, which was inspired by an undergraduate research project completed under the guidance of Professor Peter Sadler.
Further credit: Professor Sadler who wrote a short piece for theInformationDaily.com, 'Using precious metals to fight cancer', following research at The University of Warwick. 

Further reading: BBC, 'Chemists create new way to fight drug resistant cancer'.
Macmillan Cancer Support - 'Cisplatin - Cancer Information'

Friday, 6 November 2015

Has This Been Humanity's Deadliest Threat to Date?

Over the course of centuries, humans have witnessed the wrath of many deadly endemic, epidemic and pandemic diseases. Some notable examples include the uprising of small pox and the Bubonic plague. The number of deaths worldwide that have resulted are alarming. However, what is more profound is how fast the pathogens of these diseases spread in a population. In later years, the impact of these epidemics often become the subject of academic study in Medicine, in particular, epidemiology. In addition to these giants of infectious disease, there is another worth mentioning, which could be debated as 'the greatest medical holocaust in history' - the Spanish Flu of 1918.

Above: A Spanish flu ward at Fort Riley, Kansas, in 1918. (Source: The Guardian)

Caused by the H1N1 Influenza virus, the Spanish Flu was capable of rapid transmission, which resulted in it's success - 500 million people infected worldwide (one fifth of the world's population at that time (Source: Census.gov)). The fact that the infection numbers were indeed astronomically large, in the years post-pandemic, it was difficult to make an estimate of the mortality rate. Another reason is that many different countries around the world were affected by a preceding war, and different countries were affected to different extents. However, most sources indicate that the number of deaths ranged between 10-20% of those infected, i.e 50-100 million (Source: Archives.gov - The Deadly Virus). To put this into comparison, just over 17 million were killed over the duration of the Great War (Source: BBC). Despite the magnitude of destruction that the Spanish Flu inflicted, it has become a subject of lesser interest over the years. Looking back at these events, what could we learn to move ourselves forward in the medical field?


One of the great mysteries surrounding the Spanish Flu pandemic is that of the origin of the virus. Some of the latest media report that this virus is likely to have originated from the Far East, in particular, China. However, previous suggestions for the origin location range from Midwest America to France! It is generally accepted that the virus later mutated, causing the most destruction. According to the National Geographic, "new research is placing the flu's emergence in a forgotten episode of WW1: the shipment of Chinese labourers across Canada in sealed train cars." During the War, there was an increasing demand for labour, especially behind the British and French lines.


Above: Public notice for influenza in 1918 (Source: Wikipedia)


Unfortunately those that were infected often suffered unpleasant symptoms: bleeding from the nose and ears was common as well as (after autopsy) swollen hearts and lungs that had become solidified. Some figures showed that some lungs after autopsy measured up to six times their normal weight. The explanation for this is the build up of fluids (oedema) during the course of infection. This accumulation of fluid would have been a significant obstruction and gas exchange would have become increasingly difficult. It follows that as a result of this, many of those infected would die of asphyxiation. One of the physicians working at a military camp near Boston, Massachusetts in September 1918 describes the symptoms of asphyxiation one would typically have in vivid detail:

"Two hours after admission they have mahogany spots all over the cheek bones, and a few hours later you begin to see the cyanosis extending from their ears and spreading all over the face, until it is hard to distinguish the coloured men from the white. It is only a matter of a few hours then until death comes and is is a struggle for air until they suffocate. It is horrible. One can stand it to see one, two or twenty men, but to see these poor devils dropping like flies sort of gets on your nerves." 
                                                 
                                                                         - A physician stationed at Fort Devens, Boston, September 1918 (Source: Voices of the Pandemic) 

As well as these conditions that resulted from infection of the virus, often, many others would become ill from secondary infections such as pneumonia - a bacterial infection. The influenza virus is able to penetrate the respiratory system and damage the cilia and epithelial cells lining the lungs. The immunity of the infected is weakened due to the cells of the immune system losing their function. Thus, one becomes increasingly susceptible to pneumonia. 


(Above: Orginal photograph of the H1N1 virus, taken in the CDC Influenza Laboratory) 

As we know, the Spanish flu was caused by the H1N1 virus. What does this mean? Any virus that contain the letters H and N each followed by a number indicates that the virus is type A influenza. The letters H and N refer to haemagglutinin and neuraminidase respectively, the distinctive membrane proteins on the virus. Haemagglutinin binds to receptors on host cells. This causes fusion of the two membranes and deadly infiltration of the viral content. Neuraminidase acts at the end of the viral replication cycle - it 'cleaves' the new virus from the host cell. Now, the cycle is able to occur again and again, and other neighbouring cells become infected. Moreover, the proteins can actually prove very useful - they are extracted from circulating strains, purified, and use in a flu jab vaccine that is given every year.

However, what made H1N1 in 1918 such a big problem was the concept of genetic drift. This became apparent in 2005, when a group of American scientists sequenced the genome of the 1918 flu virus. The tissue sample came from a female patient who was buried in an Alaskan permafrost. The shift was gradual, initially being carried in an avian host. The H1N1 was able to mutate during the course of the pandemic, making it's infection very potent. A mutation in the genome would have caused the subsequent virus to produce subtly different variations of haemagglutinin and neuraminidase. As a consequence, antibodies produced by the host will no longer be able to bind to these proteins. The virus evades the immune response.


Above: The pathogenesis of an influenza A type virus (Source: Biological Sciences Review Volume 27, Number 4)


You might argue that perhaps only the most vulnerable would have been at risk. However the virus was evidently very potent and not discriminatory it would seem. The flu was prevalent in rural as well as urban areas - even the most remote parts of Alaska were affected! Usually, young adults tend to be the least affected when it comes these types of infectious diseases - their immune systems are generally well developed. However, for the Spanish flu, it was the exact opposite. This group tended to be severely affected, along with the vulnerable groups (elderly and young children). One astonishing statistic is that the average life expectancy of the USA dropped by twelve years during one year of the pandemic alone. (Source: Archives.gov)

Above: Age profile of deaths from Spanish flu (Source: Data from Centers for Disease Control and Prevention)

In the graph above, we can compare the deaths for each age group during the period 1911-1917 to the year 1918 - the year of the Spanish flu. What is unusual is the spike in deaths in the age group for young adults. Over the years, this has intrigued epidemiologists - however one theory that does exist to explain this oddity of flu epidemics is the 'cytokine storm'. This relates to the idea that the young and healthy have the most powerful and effective immune systems. However, during an infection with flu, the immune response can too excessive, becoming detrimental to health. Cytokines are chemical released by cells of the immune system during an infection to provide a means of cell communication. Some cytokines accelerate chemical processes, whilst others inhibit them. They also cause increased inflammation, swelling, and vasopermiability (the blood vessels become more permeable). Usually, this would help to fight the infection, however sometimes this response can come at the expense of an organ that has an oedema (and reduced blood supply). A consequence of this is tissue scarring, and then multiple organ failure. So, in the case of Spanish flu, an 'overreaction' of the immune system can indeed prove fatal (Source: Biological Sciences Review Volume 27, Number 4).


What could be done in the future? According to the World Health Organisation, the next pandemic 'will kill between 2 and 7.4 million people'. H5N1 (bird flu) is considered the most dangerous currently. In future, epidemiologists will need to keep watch for emerging epidemics that could potentially become catastrophic pandemics. In the field of infectious diseases, emphasis is being placed on prevention, more than ever before.

In addition to the reference provided above, credit should be given to Bethany Butcher who wrote an article on Spanish flu for the Biological Sciences Review April issue, 2015.
Extra reading:


Wednesday, 30 July 2014

The Complications of Obesity And Their Devastating Effects

What is becoming increasingly common in western countries such as the UK is the onset of obesity. Some would say that it has dominated health related news for the last few years. Following this, increasing numbers are likely to result in increasing concerns. What many people associate with obesity is the increasing risk of developing heart related diseases and the early development of diabetes. However what many people fail to realise is that obesity is becoming increasingly related to many different cancers. Although all these diseases could be considered equally devastating, the spread of cancer and it's effects is the cause of many funded research projects throughout the world. It is indeed of the worlds emergencies.

According to an article published in the Lancet medical journal, obesity has the potential to put people 'at greater risk of developing 10 of the most common cancers'. The study has arrived at this link through investigating the health of 5 million people which is an incredible number for a study. Additionally these people were monitored over an extended period of 7 years, which is very comprehensive in my opinion. It follows that I have increased confidence in the findings due to the sheer scale of the study - however it is always important to understand the study holistically before drawing conclusions.

It is fair to say that obesity can increase the risk of developing cancer in general with age. However what was unique about this study was that the size of a risk is dependent on the type of tumour. For example, the study found that cancer of the uterus carried the biggest risk when an individual becomes obese. Conversely leukaemia carried the lowest relative risk. Obviously men will not suffer from cancer of the uterus, so the biggest risk that is posed to obese men is gallbladder cancer, according to the study.  Scientists from the London School of Tropical Medicine found that 'each 13-16 kg of extra weight an average adult gained was linked firmly and linearly to a greater risk of six cancers'.

Furthermore, a high Body Mass Index (BMI) has been linked to higher risk of the incidence of cancer of the liver, colon and ovaries just to name a few. However what was very peculiar is that the researchers found that an increased BMI seemed to be linked with a decreased risk in prostate cancer. Of course, this only displays a correlation which doesn't always necessarily indicate a causal link, nevertheless this statistic is intriguing. Despite the links to risks with BMI, one may assume these links are sufficiently linear. But according to Dr Krishnan Bhaskaran who led the research team, "There was a lot of variation in the effect of BMI on different cancers". An example he described was that the risk of cancer of the uterus increased 'substantially' with increased BMI however this link proved more 'modest' when looking at other tumour types.

So it is evident that scientists will need to investigate the causal mechanism behind the differences in increased risk. Dr Bhaskaran suggests that "BMI must affect cancer risk through a number of different processes, depending on cancer type". Although quite vague, this statement enforces that cancer is an area of research that will need to be fully understood in the coming years in order to cause medical advances in the scientific world.


Credit to Smitha Mundasad, BBC News Health Reporter for the original article. Read more on the subject here.

Tuesday, 22 July 2014

The Ongoing Pursuit For Stem Cell Medicine

In recent times, attention has been drawn to a particular area of biological science involving the use of stem cells. In biology, these are a type of undifferentiated cells which are capable of being multipotent or even pluripotent (embryonic stem cells only). This truly remarkable characteristic has intrigued and ultimately inspired scientists to develop techniques that can be applied to the medical field.

However we must appreciate that there are two types of stem cell. Adult and embryonic. Embryonic stem cells are derived from a 'small hollow ball of cells' called a blastocyst. This is one of the immediate results of fertilisation. What scientists are interested in is the inner cell mass - these cells are undifferentiated but more importantly they are pluripotent. This means that they have the capacity to develop into any type of cell in the body. Conversely, adult stem cells are considered multipotent, meaning they have the capability to develop into one type of cell however the variety is limited. In the human body, the most common extraction point for adult stem cells is bone marrow (although many other tissues and organs are known to produce stem cells, including the brain, heart and skin). Interestingly, foetuses have also been found to have stem cells.

Some adult stem cells such as fibroblasts can actually be reprogrammed genetically for them to 'behave like embryonic stem cells'. These are known as induced pluripotent stem cells.

Another fascinating property of stem cells is that during asymmetric division, two daughter cells are produced with contrasting characteristics. One cell is the result of self-renewal, whilst the other the result of differentiation. This explains how our body is able to heal and repair itself - any type of cell can be made available to any site where it is needed. This ability for these cells to replicate themselves and differentiate is a marvel of genetics. So how is this controlled? An engaging article in a Biological Sciences Review magazine gave me an insight.

Differentiation of stem cells is dependent on 'changing the expression of the self-renewal and pluripotency control genes'. Scientists have carefully monitored which genes switch on or off during differentiation for a variety of cell types. The result is, we can identity which genes control differentiation for a vast array of cell types. An example given is that for the production of cartilage cells (chondroctyes), adult stem cells need to 'express high levels of the gene SOX-9. This gene encourages the expression of a different gene called COL2A1 as a consequence. As genes code for polypeptides, it follows that COL2A1 codes for the production of the type-2 collagen protein. Cartilage largely comprises of this protein.


When adult stem cells are used in medicine, scientists tend to use induced pluripotent stem cells (see above) as their diversity for differentiation is a significant advantage. However for medical applications in the body, sometimes we require the aid of biomaterials to supplement the use of implanted stem cells.  The example used in this article is treatment of back pain due to a slipped disc. The pain is caused by an indentation into the spinal cord by a disc, causing a compression. Intevertebral disc cells are produced by stem cells in a lab, which can them be cultured and left to proliferate. One approach to treating the condition is to 'seed' the cells into a synthetic hydrogel. This compound exists as a gel at body temperature, it is also thermosensitive. This gel can then be 'injected into the damaged disc, where it would form a gel and act like a shock absorber, similar to a natural disc'.

The potential of stem cells in medical application is exciting and promising with continuous ongoing research. Diseases such as Alzheimer's and muscular dystrophy could one day be in combat with emerging stem cell treatments to improve the lives of those who endure the pain of these conditions.


Credit to Dr Stephen Richardson, lecturer in cell tissue engineering at the University of Manchester who wrote for the Biological Sciences Review (Volume 26, Number 4)

Saturday, 19 July 2014

New Assisted Dying Bill in Review

One of the latest news stores this week is the review of the assisted dying bill, which if passed will give permission for doctors to administer doses of powerful drugs to end the lives of those whose quality of life is seriously compromised. Essentially euthanasia, this will allow people who are seriously terminally ill to consider whether they would want to sustain their lives any longer. For me, this is a topic in which people should approach with caution as it is real lives, real people, real stories that we are dealing with.

On a basic level (although I respect this isn't a simple topic at all) we are evaluating the quality of a persons life against the longevity or quantity of their life. Indeed it leaves the nation divided in opinion. Speaking to The Independent, oncologist Professor Karol Sikora  believes that the implementation of this power for doctors will result in "death squads" of doctors.

What is important to note is that assisted dying will be of significant relevance to the terminally ill who have been told the have 'less than six months to live'. If this bill is passed, it will mean doctors will have a further big responsibility, more vitally important choices to make.

Doctors in my opinion may only make up a fraction of this matter. In medicine, the patient is the paramount figure of every case - ultimately it is their choice whether to end their own lives or not. I believe they should have the choice, providing they are sane and in "the right frame of mind". No doubt, their families will have a part to play in every patient's decision.

However British Prime Minister David Cameron is concerned that if passed, the bill may cause people to be "pushed into things that they don't actually want for themselves."

Some may argue that assisted dying will help to suppress the needless suffering of the terminally ill - this could have an effect on families as well will lessened responsibility and emotional suffering perhaps.

What do people think? Well according to a 'poll for ITV this week, 70% of Britons are behind the assisted dying bill, with 10% disagreeing'.

In my view, I believe that the bill should be passed. The attention must be brought to the patients themselves. It is they who endure terrible suffering, it is they who should be given a choice.

Credit to Natasha Culzac, reporter for The Independent for the original article. Click here for more on the story.

Wednesday, 16 July 2014

Meeting the Target - The NHS and A&E

With the population as large as ever in the UK, subsequently in the last few years there has been a noticeable and increasing strain on NHS services across the board. However I believe, along with many others, that the Accident and Emergency Department can be considered to be under the biggest of pressures today. A programme on the BBC I watched recently showed exactly the effects of this population pressure on staff and patients alike. The Panorama documentary was a rather short 30 minutes, nevertheless a real eye-opener to the general public to appreciate the scale of the problem.

I encourage you to see it and I have embedded the video below:


What I found quite shocking is that many of the staff are under constant pressure from the many patients who arrive to the hospital every hour. However it isn't just the local pressure - government-set deadlines and targets ensure the conveyer belts of NHS services are rolling quickly. One doctor in the film says "it's a more stressful place to work than it once was"when referring to the A&E Department of today.

Judging from the documentary, the staff seem stressed, however I deeply respect their professionalism as when dealing with the wide variety of patients, they control their emotions. This is vital when dealing with the public and representing an organisation as important as the NHS. One example from the clip I especially remember is when a heavy alcoholic was admitted to A&E. His rowdy, agitated and rather unpredictable manner meant the nurses in particular were dealing with a tough patient. Refraining from raising their voice too much, they managed to control the patient. In fact if he had turned very aggressive, the staff may have been at risk from harm. The number of alcoholics and drug abusers admitted to A&E is alarming, and they are transported to hospital 'around the clock'. For this hospital alone there are '3 to 4 overdoses a day'.

The pace at which staff need to work is tremendously quickly, whilst being efficient. It shows how training is vitally important to sustain such roles in the health service.

In the video, I was rather interested to see that one GP said that she once wanted to work for the A&E department of the NHS as it suited here own interests. However she ended up settling for a job less manic as a GP, as she no longer wanted to be part of a "sinking ship". She is clearly an experienced health professional, and I respect here view which is why I appreciate the scale of the problem we face in A&E.

One of the major problems in fact is the limited number of hospital ward beds available to patients after they leave the A&E department. Some patients are left to wait hours. The large number of patients poses a dilemma. The NHS need to strike a balance between treating as many people as possible and giving each patient the thorough and correct care they need to make a good recovery.

Solutions to the problem are already being implemented. However many people simply aren't aware of alternative healthcare services that have been made available by the NHS. Walk-in centres and dialling 111 are just a named couple that one could use in out-of-hours for GP's instead of visiting A&E. More awareness is needed to inform the public that personal health advice is available very readily on a local level and is easily accessible.


Sunday, 13 July 2014

New Blood Test For The Detection of Alzheimer's

One of the big health stories that have emerged this week is the formulation of a new blood test which will have the potential 'to detect which people with failing memories will go on to develop Alzheimer's disease'. When I quote 'failing memories', what I am referring to is mild cognitive impairment. Statistically, 60% of those who have this form of memory loss go on to develop Alzheimer's. For the general public, it is imperative to note that this a diagnostic solution, not a cure. Nevertheless, getting a correct diagnosis with vast amounts of research can lead on to the synthesis of new drugs which can be used to treat the disease. Increases in research funding would allow scientists to draw closer to a solution - but this is difficult as scientific research isn't advancing at a rate we might think. There are inevitably restrictions due to funding and legal issues.

Only 'after a decades work', has this new blood test been derived which shows the unbelievable timescale of innovation. The test involves looking at 10 sets of proteins that are suspended in the blood. Kings College London in conjunction with Proteome Sciences have published the study. The claim is that this test 'can predict the onset of Alzheimer's in the next 12 months in people with memory problems with an accuracy of 87%'. The cost of such a test can be estimated at around £100 to £300.


Instantly in my brain I question the "87%" accuracy as I'm concerned that for a test as significant as this, a very high high accuracy is desired in order to diagnose the right people. Alzhiemer's and other forms of dementia are one of the most common diseases in our society - according to David Cameron, it "stands alongside cancer as one of the greatest enemies of humanity". I fear he is right. With an ageing population and with the development of the latest treatments to prolong life expectancy, epidemiological evidence says the incidence of these diseases are rising.


With this new test, the key turning point is that people will be identified as having the potential to go on to develop Alzheimer's. Not simply diagnosing those who have Alzheimer's. This is crucial. Read enough into the disease and you'll probably realise that Alzheimer's is very complex. This is why we need to diagnose people at the earliest opportunity. Professor Simon Lovestone from Kings College London puts it perfectly: "Alzheimer's begins to affect the brain many years before patients are diagnosed with the disease. Many of our drug trials fail because by the time patients are given the drugs, the brain has already been too severely affected".


The scientists in the investigation wrote for the journal Alzheimer's and Dementia, and investigated in a variety of proteins that have been linked to Alzheimer's before. Blood samples were taken from 1148 individuals. A large sample some may think, but the size of the problem we are confronting means the next stage for this test is for it to be trialled on around 5000-10000 people. 


A larger sample size means more reliability which will make this study more valid and thus promising. Also getting more accurate results with the test will reduce the risk of misdiagnosis which is outstandingly important. 

Personally I believe this to be positive and promising news, but we need to be sure that this will work. I hope that in the end this could develop into effective treatment for one of the most devastating diseases that exist in our society today. 


Credit to Sarah Boseley, health editor for The Guardian on the original article. More on the story can be followed here.


Sunday, 29 June 2014

Beginnings...

With my growing interest for medicine over the last few years, I have arrived at a point where I think it may be appropriate to express some of my views on today's changing events in the medical field. The field of medicine is one of profound innovation yet very personal to many. It is greatly affected by economics and politics - our NHS system has had significant reforms in recent times. Changes in the structure of the NHS have had a knock-on effect even right down to the patient level, whether it is receiving the right treatment or whether one can afford the treatment at all.

In fact one of the most controversial issues surrounding the NHS and the government is whether the NHS as an organisation will enter privatisation. When most people think of privatisation, they are reminded of the US-style health insurance 'fee for service' plans. For many this may mean no easy access to essential healthcare anymore, but could indicate 'big bucks' for emerging private health companies such as Virgin Care, a sub-category of Richard Branson's Virgin empire. An essay I have written on whether the NHS should be privatised can be seen here. I encourage a read to anyone who isn't particularly sure of what privatisation is and it's implications.

Also I will look forward to commenting on any medically related books I read that spark an interest in me.